How the Anion Gap Is Measured
The anion gap is a derived value that assists clinicians understand acid-base balance and spot unmeasured anions in the blood. It is most often obtained from a basic electrolyte panel using serum sodium, serum chloride, and serum bicarbonate. In practical terms, the anion gap is a tool for laboratory interpretation that can suggest metabolic acidosis even before the full cause is known.
The calculation represents the difference between the main measured cations and anions in serum. Because the body contains many charged particles that are not directly measured, the anion gap calculation can uncover hidden acids from acid accumulation, toxins, or organ dysfunction. A higher-than-expected value often suggests a pathologic process such as high anion gap metabolic acidosis, while a normal value may lead clinicians to consider other causes of illness.
An anion gap calculator simplifies this step and lowers the chance of arithmetic mistakes during clinical assessment. In a toxicology setting, that efficiency matters because the result may trigger toxicology screening, more urgent lab testing, or immediate treatment. Although the number itself is simple, its interpretation can be critically significant.
Why Toxic Ingestion Can Raise the Anion Gap
Toxic ingestion is often a major cause of elevated anion gap because many poisons generate acids directly or alter metabolism in ways that boost acid production. In these cases, the body accumulates unmeasured anions that widen the calculated gap. This pattern is essential to identifying high anion gap metabolic acidosis in a poisoning workup.
Some exposures, especially toxic alcohols, are well-known anion gap in chronic kidney disease causes. Methanol and ethylene glycol are metabolized into acidic compounds that lead to metabolic acidosis. Early after ingestion, the osmolar gap may be elevated before the anion gap rises, while later the anion gap can become markedly abnormal as toxic metabolites accumulate. This timing issue is one reason why both values are useful in clinical assessment.
Other poisonings can raise the gap through lactic acidosis, impaired tissue oxygen delivery, seizures, shock, or mitochondrial dysfunction. Salicylate toxicity can also produce complex changes in acid-base balance, sometimes combining respiratory alkalosis with metabolic acidosis. The underlying process may involve increased lactate, impaired clearance, or the addition of other acids into circulation.
In many cases, the anion gap is not the diagnosis itself but a diagnostic signal. It helps clinicians recognize that something is driving acid-base abnormality and may warrant immediate toxicology evaluation. This makes it especially useful when symptoms are nonspecific, such as nausea, altered mental status, tachypnea, or unexplained systemic toxicity.
How to Use an Anion Gap Calculator
An anion gap calculator typically needs only the values from an electrolyte panel: serum sodium, serum chloride, and serum bicarbonate. The common formula is sodium minus the chloride value and bicarbonate. The resulting figure approximates the difference between measured cations and anions and helps screen for hidden acid load.
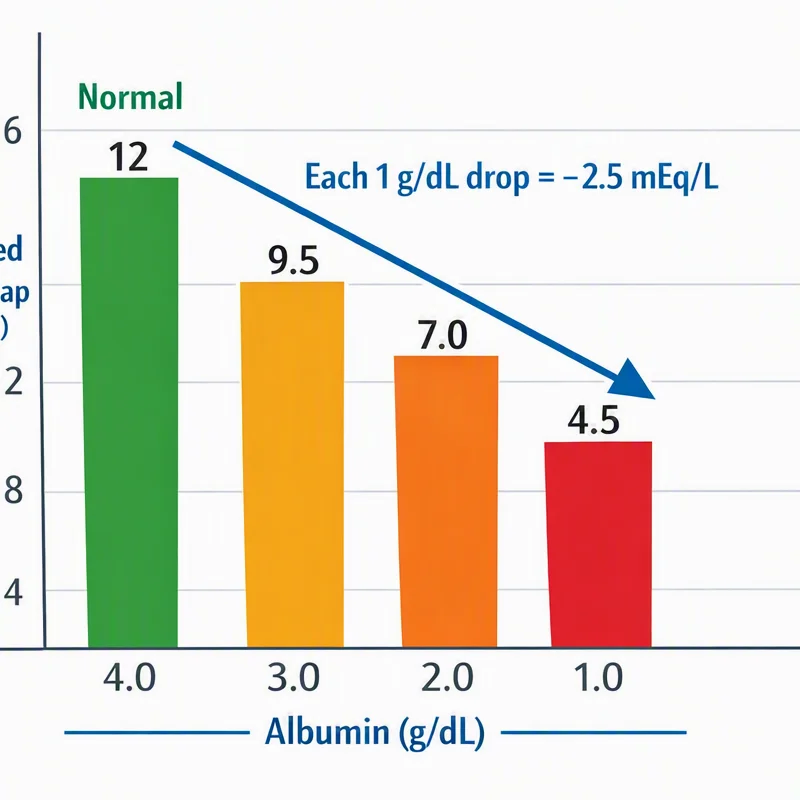
For toxic ingestion, calculator use should go beyond the raw number. A careful review of albumin is important because low albumin lowers the measured gap and can hide clinically meaningful abnormalities. That is why many clinicians calculate a corrected anion gap. Albumin correction improves sensitivity when evaluating possible poisoning, especially in hospitalized or critically ill patients with hypoalbuminemia.
Using the calculator in sequence can promote timely decision-making:
- Ensure the electrolyte panel values are current and internally consistent. Determine the raw anion gap. Review albumin and determine the corrected anion gap if needed. Measure the result with the expected diagnostic threshold for concern. Evaluate the result alongside symptoms, history, and other studies.
This process improves laboratory interpretation and helps align the gap with the broader clinical picture. For example, a patient with suspected ingestion may have an only mildly elevated raw gap but a clearly abnormal corrected value. That distinction can raise the level of concern for toxic ingestion and guide next steps in urgent management.
Typical Toxic Sources of Raised Anion Gap
Several toxic poisonings are frequently associated with raised anion gap and elevated anion gap metabolic acidosis. The key include methanol, ethylene glycol, salicylates, and situations with excess ketones. Each produces a somewhat more different pattern, but each one can be associated with acid-base derangements severe enough to require prompt recognition.
Methanol is metabolized into formic acid, which contributes to severe acidosis and can also cause visual symptoms. Ethylene glycol is converted to glycolic and oxalic acids, which may injure the kidneys and contribute to renal failure. Finding of crystals, worsening creatinine, or neurologic changes can reinforce suspicion, but the anion gap often provides the initial laboratory clue.
Salicylates can cause a mixed pattern with early https://blogfreely.net/schadhsgck/how-aspirin-toxicity-alters-the-anion-gap respiratory alkalosis and later metabolic acidosis. The acid-base picture may be confusing unless the clinician considers toxicology. Ketones are another major source of elevated gap, especially in diabetic ketoacidosis, alcoholic ketoacidosis, or starvation-related states. In these situations, ketoacidosis and the buildup of ketone bodies play a role to the abnormality.
It is worth remembering to remember that toxins may act indirectly. Some exposures cause vomiting, hypoperfusion, seizure activity, or hypoxia, which can drive lactic acidosis. Others impair metabolism and increase acid production without obvious early symptoms. A calculated gap can therefore be a valuable bridge between nonspecific symptoms and a targeted toxicology diagnosis.
How to Understand Values in Diagnostic Context
The anion gap should by no means be considered in isolation. A increased result indicates metabolic acidosis, but the next step is to determine whether the pattern matches a specific acid-base disorder. In toxic ingestion, the most important supporting studies often include the osmolar gap, an arterial blood gas, and a repeat electrolyte panel to confirm trends.
The osmolar gap can be especially helpful at an early stage in suspected exposure to toxic alcohols. A elevated osmolar gap suggests unmeasured osmotically active substances, while a rising anion gap indicates accumulation of acidic metabolites. Together, these findings increase the suspicion for methanol or ethylene glycol poisoning.
An arterial blood gas gives direct information about pH, bicarbonate, and respiratory compensation. It helps identify whether there is severe acidemia, whether ventilation is compensating appropriately, and whether a mixed disorder is present. In a patient with poisoning, that data can guide airway, ventilation, and antidotal decisions.
Context matters equally with numbers. Tachypnea, visual complaints, altered mentation, abdominal pain, renal injury, or hemodynamic instability all raise concern for systemic toxicity. When the lab pattern fits and the history is uncertain, the combination of anion gap, osmolar gap, and blood gas findings can warrant immediate toxicology consultation and treatment.
Drawbacks and Pitfalls of Anion Gap Calculation
Although useful, the anion gap has major limitations. A particularly common one is hypoalbuminemia. Since albumin is a major unmeasured anion, low levels can make a truly abnormal gap appear normal. This is why a corrected anion gap is so valuable in critically ill or nutritionally depleted patients.
Another pitfall is mixed acid-base disorders. A patient may have both a high anion gap metabolic acidosis and a concurrent metabolic alkalosis or respiratory disturbance, which can obscure severity. This is where the delta gap becomes helpful. The delta gap compares the change in the anion gap to the change in bicarbonate and can uncover hidden alkalosis or additional acid-base processes.
Lab error is another concern. Blood cell breakdown, specimen issues, transcription problems, or delays in processing can distort the values used in the calculation. If the result does not match the clinical picture, repeating the test may be necessary before making major decisions. That caution is especially important when a poisoning workup is already underway.
In the end, a normal anion gap does not fully exclude toxic exposure. Some ingestions are early in their course, some are partially treated, and some produce mixed patterns. For that reason, clinicians should treat the calculator as a reference tool rather than a standalone rule-out test. The best practice is to combine laboratory interpretation with symptoms, exposure history, and serial reassessment.
If an Increased Anion Gap Requires Immediate Action
An high anion gap in the setting of suspected poisoning may signal a time-sensitive emergency. If there is altered mental status, severe acidemia, visual symptoms, kidney injury, or hemodynamic instability, the patient needs emergency evaluation right away. Rapid communication with the poison center can help confirm likely exposures and inform antidotal or supportive treatment.
Urgent action becomes even more important when toxic alcohols are suspected because delays can worsen outcomes. In certain situations, hemodialysis may be indicated to remove the toxin and correct severe acidosis. This is especially relevant for methanol and ethylene glycol poisoning, as well as for profound metabolic derangement that is not responding to initial measures.
Clinicians should also think beyond the number itself. A patient with a rapidly rising gap, worsening pH, or supportive osmolar gap findings may need urgent treatment even before confirmatory levels return. Prompt antidotal therapy, aggressive supportive care, and frequent reassessment are often central to urgent management.
If there is any uncertainty, the safest course is to escalate care. Severe high anion gap metabolic acidosis can deteriorate quickly, and a delayed response may allow more toxin metabolization and tissue injury. In practice, anion gap calculator is most valuable when it helps identify the point at which observation is no longer enough and urgent intervention is needed.
Common Questions
What counts as a normal anion gap?
The anion gap reference interval varies by the laboratory technique, but a typical normal anion gap is often approximately the low to mid teens. Because multiple analyzers and reference intervals can vary, the local lab range should be used when available. In toxicology, even a borderline increase can matter if symptoms or exposure history suggest poisoning.
How does toxic ingestion affect the anion gap?
Poisonous swallowing can elevate the anion gap by bringing in acids to the blood, increasing acid buildup, or impairing metabolism so that acids such as lactate and ketone bodies collect. This results in high anion gap metabolic acidosis. Exposures like methanol, ethylene glycol, and salicylates are important cases.
Which toxic alcohols lead to a high anion gap?
The most important toxic alcohols associated with a raised anion gap are methanol and ethylene glycol. They produce acidic metabolites that cause metabolic acidosis. A increased osmolar gap may be seen early, followed by a rising anion gap as the metabolism progresses.
Why is it important to albumin be used to correct the anion gap?
Albumin protein is a key unmeasured anion, so reduced levels can reduce the observed gap and hide clinically significant disease. Calculating a adjusted anion gap refines interpretation in patients with low albumin levels. This is particularly helpful in critical illness, where the raw number may underestimate the severity of a toxicologic problem.
When should someone with an elevated anion gap get urgent medical attention?
Immediate attention is required when an elevated anion gap occurs with signs of exposure, disorientation, rapid breathing, severe vomiting, changes in vision, kidney injury, or worsening illness. As these can signal dangerous systemic toxicity, the patient should get emergency evaluation. Should a toxic exposure is possible, contacting a poison center as soon as possible is recommended, and hemodialysis may be needed in severe cases.