Understanding Normal Anion Gap Metabolic Acidosis?
Normal anion gap metabolic acidosis is an acid-base imbalance in which the blood becomes more acidic because bicarbonate is depleted or not properly regenerated, but the anion gap remains within the expected range. It is also commonly called hyperchloremic metabolic acidosis or non-anion gap acidosis, because the drop in bicarbonate is often matched by a rise in chloride.
In metabolic acidosis, the body has too much acid or too little buffer. In the normal anion gap form, the main issue is usually bicarbonate loss rather than accumulation of unmeasured acids. That is why the pattern often includes a low serum bicarbonate and increased chloride, while the calculated anion gap remains normal. This pattern can develop from gastrointestinal loss, kidney dysfunction, or medication effects.
The clinical presentation may include rapid breathing from compensatory respiration, fatigue, weakness, nausea, or signs of an electrolyte imbalance. Recognizing the pattern is important because the diagnostic approach differs from that used for high anion gap acidosis. A focused laboratory evaluation can help identify whether the cause is in the gut, the kidney, or another source of bicarbonate loss.
Why an Anion Gap Calculator Aids in Acid-Base Analysis
An anion gap calculator is a practical aid for acid-base analysis because it enables clinicians understand basic chemistry values in relation. The calculator uses sodium, chloride, and bicarbonate values from serum electrolytes to estimate the anion gap and see whether the acidosis is likely a non-anion gap pattern or a high gap pattern.
In a standard formula, sodium is weighed against chloride and bicarbonate. When chloride rises as bicarbonate falls, the gap may appear normal, suggesting hyperchloremic acidosis. This pattern can be very helpful when the cause is not obvious from the clinical presentation. A calculator does not take the place of clinical judgment, but it provides a structured diagnostic approach.
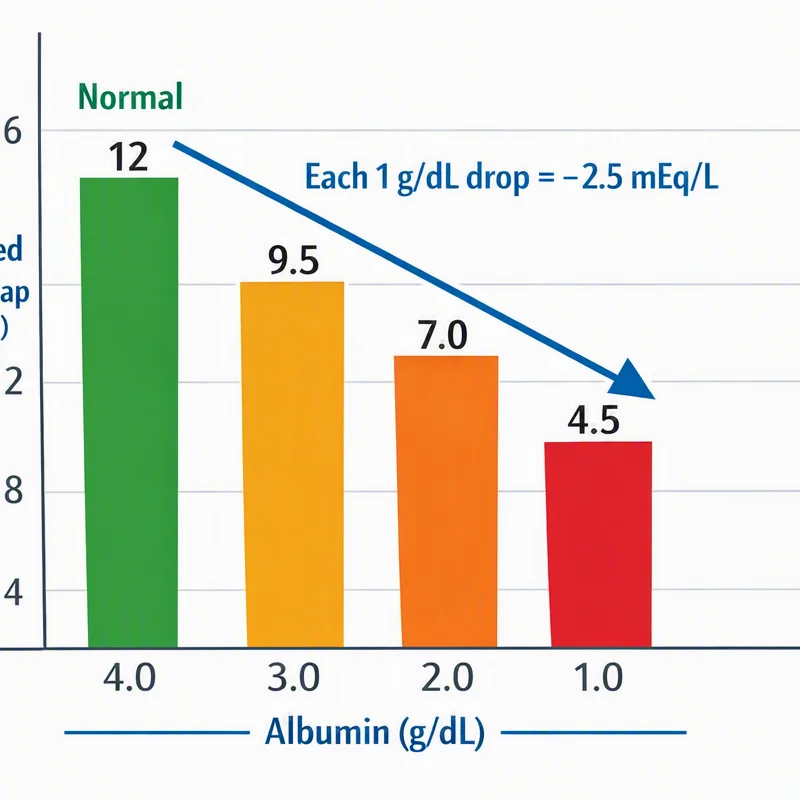
Using an anion gap calculator also enables clinicians avoid missing mixed disorders. For example, a patient may have metabolic acidosis with albumin changes that affect interpretation of the anion gap. Because albumin contributes to the measured gap, low albumin can make a high-gap problem look less significant than it truly is. That is why the anion gap should always be interpreted with the full chemistry panel and the rest of the acid-base picture.
In practice, the calculator can guide the next steps: if the gap is normal and chloride is elevated, the likely issue is often bicarbonate loss, impaired renal acidification, or another cause of chloride retention. That refines the search and boosts the efficiency of the workup.
The Most Common Reasons of normal anion gap metabolic acidosis
The main reasons of normal anion gap metabolic acidosis are conditions that reduce serum bicarbonate without producing a large burden of unmeasured acids. The primary mechanisms include diarrhea and other gastrointestinal causes of bicarbonate loss from the gut, renal tubular acidosis, and medication or toxin exposure. Many of these disorders lead to hyperchloremia because chloride rises as bicarbonate falls.
Understanding the mechanism helps structure the differential diagnosis. If bicarbonate is lost through the gut, the kidneys usually respond by increasing acid excretion. If the kidneys are the problem, urinary acidification is impaired, and bicarbonate may be wasted or not regenerated appropriately. Medication and toxin causes can affect renal handling of acid and electrolytes, producing a similar lab pattern.
When reviewing the differential, it helps to think in terms of cause: GI losses, kidney tubular defects, or exogenous exposures. Each can produce a similar chemistry pattern, but the associated clues often differ enough to point toward the correct diagnosis.
GI Causes
Diarrhea is one of the most frequent causes of normal anion gap metabolic acidosis. The gut contains bicarbonate-rich fluid, so ongoing stool losses can lead to significant bicarbonate loss. This is a classic example of GI loss causing hyperchloremic metabolic acidosis.
An ileostomy can also cause bicarbonate depletion, especially when output is high. Similarly, a pancreatic fistula can drain bicarbonate-rich secretions and contribute to acidosis. These conditions are often recognized by the history: increased output, dehydration, weight loss, or evidence of fluid depletion.
In gastrointestinal causes, the kidneys are usually functioning normally and respond by conserving bicarbonate and increasing urinary acid excretion. That distinction becomes important when interpreting the urine anion gap later in the evaluation. If the kidneys are responding appropriately, the urinary pattern typically reflects increased ammonium excretion.
Kidney-Related Causes
Renal tubular acidosis is a significant kidney-associated cause of normal anion gap metabolic acidosis. In this set of conditions, the kidneys have difficulty making acidic the urine or managing bicarbonate properly. The result is a continuous acid-base disorder even when the glomerular filtration rate may be mostly preserved early on.
Type 1 renal tubular acidosis, also called distal renal tubular acidosis, occurs when the distal tubule cannot properly release hydrogen ions. This impairs renal acidification, leading to acid retention and often a delta delta metabolic acidosis formula high urine pH. Patients may also develop low potassium and problems related to chronic acidosis.
Type 2 renal tubular acidosis, or proximal renal tubular acidosis, involves the proximal tubule and is commonly associated with bicarbonate wasting. The proximal tubule fails to reabsorb filtered bicarbonate effectively, so bicarbonate is lost in the urine until a new steady state is reached. This can cause persistent metabolic acidosis and may coexist with other proximal tubular defects.
Type 4 renal tubular acidosis is different because it is often linked to impaired aldosterone activity or resistance. It is commonly associated with hyperkalemia and reduced ammonium production, which leads to impaired acid excretion. When potassium is high or inappropriately normal in the setting of acidosis, type 4 disease should be considered.
These renal causes reflect actual kidney dysfunction at the tubular level, even when other parts of the kidney may appear mostly intact. The pattern can be not obvious, so blood and urine studies are often necessary to differentiate renal tubular defects from GI causes.
Medication and Toxin Causes
Some medications and toxins can produce normal anion gap metabolic acidosis by interfering with renal handling of bicarbonate or acid. Acetazolamide is a common medication cause because it inhibits carbonic anhydrase in the proximal tubule, promoting bicarbonate loss and causing a hyperchloremic pattern.
Amphotericin B can harm renal tubules and impair acidification, sometimes leading to renal tubular dysfunction and electrolyte problems. This may resemble a renal tubular acidosis pattern with low bicarbonate and abnormalities in potassium and other electrolytes.
Toluene exposure is an additional toxin-related cause. It can create complex acid-base changes and may present with a normal anion gap pattern, especially when chloride rises as bicarbonate falls. A careful exposure history is essential because the lab pattern alone may not reveal the source.
Medication and toxin causes are often overlooked unless the diagnostic approach includes a detailed review of prescriptions, over-the-counter agents, occupational exposures, and substance use. In the right context, these causes should be prominent in the differential.
How to Differentiate Typical Anion Gap from Increased Anion Gap Acidosis
Differentiating metabolic acidosis with a normal anion gap from elevated anion gap acidosis is one of the most important steps in interpreting acid-base status. In normal-gap acidosis, the main pattern is usually low bicarbonate with increasing chloride, resulting in hyperchloremic acidosis. In high gap disorders, unmeasured acids accumulate and increase the gap.
Causes of a high anion gap include lactic acidosis and ketosis. These conditions add acidic byproducts to the blood, so the bicarbonate decreases without the same matching rise in chloride. That creates a broadened anion gap rather than a normal one. When you see a low bicarbonate level, checking the anion gap helps determine whether the problem is loss of buffer or acid buildup.
Albumin matters here because it is a important unmeasured anion. Low albumin can reduce the expected anion gap and mask a high-gap process. That means a patient with significant lactic acidosis or ketosis may look like they have a less striking gap if the albumin is reduced. Interpreting the chemistry panel without considering albumin can lead to diagnostic error.
A useful diagnostic strategy is to review the serum bicarbonate, calculate the anion gap, and then decide whether the picture matches a normal-gap or high gap disorder. If the anion gap is normal and chloride is high, think of hyperchloremic metabolic acidosis. If the gap is elevated, look for lactic acidosis, ketosis, toxins, renal failure, or mixed disorders. This is where an anion gap calculator is especially valuable as part of the broader evaluation.
Important Lab Findings and Medical Signs
The most useful clues in normal anion gap metabolic acidosis come from integrating blood chemistry, urine testing, and the overall clinical picture. An arterial blood gas verifies acidemia and helps measure respiratory compensation. Serum studies show low bicarbonate, and the chemistry panel often reveals elevated serum chloride.
The urine anion gap is especially helpful when trying to separate GI bicarbonate loss from renal causes. A negative urine anion gap often points to appropriate ammonium excretion, which is more consistent with diarrhea or another GI source. A positive or inappropriately nonnegative value can indicate impaired urinary ammonium excretion, which points more toward renal tubular acidosis.
Potassium levels also provide important clues. Low potassium may be seen with diarrhea, type 1 renal tubular acidosis, and type 2 renal tubular acidosis. High potassium is more suggestive of type 4 renal tubular acidosis. Because potassium shifts affect symptoms and treatment, it should always be reviewed alongside bicarbonate and chloride.
Clues from the history are also important as the laboratory evaluation. Ongoing stool losses, an ileostomy, a pancreatic fistula, recent use of acetazolamide, exposure to amphotericin B, or inhalational exposure to toluene can quickly narrow the anion gap in chronic kidney disease cause. A careful diagnostic approach integrates the acid-base pattern, the medication list, and the patient's volume status.
When to Seek Further Medical Evaluation
Additional medical evaluation matters when acidosis is long-lasting, unexplained, or associated with concerning symptoms. Persistent acidosis can signal ongoing bicarbonate loss, unresolved renal tubular dysfunction, or a chronic disorder that needs specific treatment. Repeated abnormalities should not be considered as temporary.
Anyone who with suspected kidney disease should be assessed more carefully, especially if the acid-base disorder is accompanied by abnormal creatinine, reduced urine concentrating ability, or changes in potassium. Tubular disorders may appear before major changes in overall kidney function, so early recognition matters.
An obvious electrolyte imbalance or signs of dehydration should require prompt attention. Volume depletion can worsen acid-base disorders and make symptoms worse. Weakness, lightheadedness, confusion, palpitations, or severe diarrhea are all reasons to obtain timely evaluation.
Because normal anion gap metabolic acidosis has multiple causes, follow-up testing may include repeat serum electrolytes, urine studies, and a more detailed look at medications and exposures. The goal is to identify the source of bicarbonate loss and treat the underlying problem, not just the abnormal lab value.
Common Questions
What is normal anion gap metabolic acidosis?
Hyperchloremic metabolic acidosis is a type of acid-base disorder in which the blood bicarbonate level is low, but the anion gap stays normal. It is often called hyperchloremic acidosis because chloride rises as bicarbonate falls. Common causes include diarrhea, renal tubular acidosis, and certain medications.
What are some the most common causes of normal anion gap metabolic acidosis?
The most common causes are diarrhea and other forms of intestinal bicarbonate loss, RTA, and medication or toxin exposure. Examples include ileostomy, pancreatic fistula, acetazolamide, amphotericin B, and toluene.
In what way does an anion gap calculator help diagnose acidosis?
An anion gap calculator uses sodium, Cl, and bicarbonate values from serum electrolytes to determine whether the acidosis is a normal anion gap or high gap disorder. This helps shape the diagnostic approach and can point toward hyperchloremic acidosis, lactic acidosis, ketosis, or mixed patterns.
How can diarrhea cause normal anion gap metabolic acidosis?
Loose stools can cause normal anion gap metabolic acidosis because stool contains bicarbonate. When the body loses bicarbonate through the intestines, serum bicarbonate falls and chloride rises to maintain electrical balance. This produces a classic chloride-rich pattern with a normal anion gap.
What lab tests help distinguish renal tubular acidosis from other causes?
Helpful tests include an ABG, serum electrolytes, potassium, serum chloride, and the urine anion gap. These results help determine whether the problem is due to GI bicarbonate loss or impaired renal acidification from tubular acidosis. Albumin should also be considered when interpreting the anion gap.